(HealthDay News) -- People who get to a hospital no more than an hour after having the first symptoms of a stroke are twice as likely to get the powerful clot-dissolving drug that is the first line of treatment, a new study finds.
Of the more than 100,000 people treated for stroke at American hospitals, 27.1 percent of those whose treatment began within a hour of the first symptoms received tissue plasminogen activator (tPA), according to a report to be delivered Wednesday at the American Stroke Association's International Stroke Conference, in San Diego.
Only 12.9 percent of those arriving between one and three hours of symptom onset received the drug, the study found.
The study results "are both good news and bad news," said study author Dr. Jeffrey L. Saver, director of the stroke center at the University of California, Los Angeles. "The good news is that the message is getting through to a partial extent. We're getting early treatment to a lot more people than we ever expected. The bad news is that only about a quarter of patients are getting to hospitals within an hour of having stroke symptoms."
The results apply only to those hospitals in the American Heart Association's "Get With the Guidelines" program, Saver noted.
Today's report did not discuss the outcome of quick treatment, Saver added. But preliminary analysis indicates that "for every 100 patients treated, 30 benefit and three are harmed," he said.
Use of tPA is the only approved treatment for the 80 percent or more of strokes caused by blockage of a brain artery by a blood clot. (The others are the result of an artery rupture.) But the drug must be used within three hours after stroke symptom onset.
Get With the Guidelines-Stroke is the stroke association's program aimed at increasing appropriate use of tPA therapy for ischemic strokes, those caused by blood clots.
Saver and his colleagues looked at the records of 106,924 people treated for ischemic strokes at 905 hospitals. They found that 28.3 percent of them arrived within 60 minutes of stroke onset, 31.7 percent arrived one to three hours after symptoms started, and 40.1 percent arrived more than three hours after symptoms started.
That last number indicates that "we have a great deal of additional work to do in educating the public and stroke center staffs," Saver said in a statement. "For every minute in which blood flow is not restored, nearly 2 million additional blood cells die."
Stroke symptoms include sudden numbness or weakness of the face, arm or leg, especially on one side of the body; sudden trouble speaking or understanding; sudden trouble seeing in one or both eyes; or sudden, severe headache.
When such symptoms occur, emergency help should be sought by calling 911 or a local emergency medical service number, the stroke association recommends.
In the study, those people who arrived at a hospital within an hour of symptom onset were more likely to suffer serious brain damage, indicating that the symptoms which led to them seeking help were more severe, the researchers said.
The Get With the Guidelines-Stroke program now covers more than 800,000 people treated at more than 1,400 hospitals, said study co-author Dr. Lee Schwamm, an associate professor of neurology at Harvard Medical School.
"This data registry can contribute significantly to our understanding of acute stroke care and outcomes," he said in a statement.
About 800,000 Americans have strokes each year, and about 300,000 die of them.
More information
Stroke symptoms and what to do about them are described by the American Heart Association.
Showing posts with label stroke. Show all posts
Showing posts with label stroke. Show all posts
Thursday, February 19, 2009


Thursday, August 28, 2008
Fat Cells in Obese People Are 'Sick'
 (HealthDay News) -- Fat cells in obese people are "sick" compared to those in lean people, a new study shows.
Published in the September issue of Diabetes, a group of researchers from the Temple University School of Medicine analyzed fat samples from the upper thighs of six lean and six obese people.
They found significant differences in the fat cells of the obese participants compared with the lean participants.
"The fat cells we found in our obese patients were deficient in several areas," study author Guenther Boden, the Laura H. Carnell Professor of Medicine and chief of endocrinology, said in Temple press release.
Boden said that the obese people's fat cells showed stress on the endoplasmic reticulum (ER), which helps cells synthesize proteins and monitor how they are folded. When the ER is stressed, Boden explained, it produces several proteins that ultimately lead to insulin resistance. Insulin resistance, in turn, plays a major role in the development of obesity-related conditions.
The differences in the fat cells between obese and lean people may help explain the link between obesity and a higher risk of diabetes, heart disease, and stroke, Boden theorized.
More information
The National Heart, Lung, and Blood Institute has more about overweight and obesity.
Wednesday, August 20, 2008
Vitamin B, Folate Supplements Won't Help Heart
 (HealthDay News) -- A study to determine whether folic acid and vitamin B supplements help the heart has been cut short, because the pills weren't doing any good and might have even caused participants harm.
"This confirms what a lot of recent studies have found -- no benefit of taking vitamin B supplements to reduce the risk of heart disease, and it raises a few red flags," said Alice H. Lichtenstein, Gershoff professor of nutrition at Tufts University, Boston.
In the new study, reported in the Aug. 20 issue of the Journal of the American Medical Association, physicians at Haukeland University Hospital in Bergen, Norway, enrolled almost 3,100 volunteers. Three-quarters of them took various doses of vitamin B and folic acid (which is chemically a B vitamin), while the others got a placebo, an inactive substance.
The study was ended early, after an average follow-up of 38 months, because "we could not detect any preventive effect of intervention with folic acid plus vitamin B12 or with vitamin B6 on mortality or major cardiovascular events," the researchers reported.
They did find a slight reduction of stroke, but also a slight increase of cancer in those taking folic acid, but neither of these results reached statistical significance. The study was ended, because another Norwegian study of folic acid and vitamin B supplementation has also hinted at an increased incidence of cancer among users.
But the real bottom line here, according to Lichtenstein, is that "there is no evidence that individuals should take B vitamins to decrease the risk of heart disease, and there may be some evidence that they shouldn't."
The trials were initiated, because observational studies did link high blood levels of a protein called homocysteine with an increased risk of cardiovascular disease. In the new study, homocysteine levels did go down by 30 percent over the course of three years in people taking folic acid and vitamin B. However, there was no related effect on the risk of cardiovascular events.
So, "the observational data was great, but the interventional studies were negative," Lichtenstein said.
Food in the United States is routinely fortified with folic acid, because it reduces the incidence of a specific class of birth defects called neural tube defects. Folic acid is a synthetic form of folate, a B vitamin found in many fruits and vegetables.
"We have been optimistic about the role of antioxidants such as vitamin B in preventing heart disease, yet many of these large trials have shown that there is no benefit," said Dr. Suzanne Steinbaum, director of women and heart disease at Lenox Hill Hospital in New York City.
It's hard to say whether the reduction in cardiovascular disease seen in some observational trials was caused by vitamin supplementation or because "people taking the supplements have good lifestyles in general," Steinbaum said.
It is also possible that the benefits of vitamin supplements show up only after many years, Steinbaum said. She does recommend a daily multivitamin pill. "But at this point, it is certainly hard to recommend extra supplements when we don't have proof of benefit," Steinbaum said. "What we can recommend is a diet with fruits and vegetables that have antioxidant vitamins in them," she said.
More information
There's more on folic acid supplementation at the U.S. Department of Health & Human Services.
Sunday, August 03, 2008
Video Consultations Effective for Stroke Treatment
 (HealthDay News) -- More accurate decisions about treatment of Stroke patients in remote locations can be made using telemedicine consultations, compared with telephone consultations, according to U.S. researchers.
Telemedicine includes real-time, two-way audio and video and digital imaging and communications.
The study included 222 adult stroke patients at four remote sites in California who were randomly assigned to telemedicine (111 patients) or telephone consultation (111 patients) to assess their suitability for treatment with thrombolytic drugs.
Correct treatment decisions were made in 98 percent of telemedicine consultations and in 82 percent of telephone consultations. Thrombolytics were given to 31 percent of patients in the telemedicine group and to 25 percent of patients in the telephone group.
After three months, both groups had similar rates of stroke recurrence or death. But this could be because the study was halted early, because it was clear that telemedicine was far superior when making treatment decisions, the study authors said.
"The results of this trial show that telemedicine is efficacious for making acute medical decisions. Stroke telemedicine is widely implemented and discussed, but despite its dissemination, its efficacy has not previously been shown. Our results support the use of telemedicine to make urgent treatment decisions, such as whether to use thrombolytic therapy for acute stroke," wrote Dr. Brett C. Meyer, of the University of California, San Diego, School of Medicine Stroke Center, and colleagues.
The study was published online Sunday in The Lancet Neurology and was expected to be in the September print issue of the journal.
More information
The U.S. Food and Drug Administration has more about stroke.
Friday, May 02, 2008
Hypertension Takes Huge Toll in Developing Countries
 (HealthDay News) -- Roughly 80 percent of high blood pressure-related deaths in the world occur in developing nations, a new study by New Zealand researchers shows.
Once regarded as a problem only in high-income countries, high blood pressure is now a global problem that affects both rich and poor nations, the researchers said.
The researchers calculated that 7.6 million premature deaths (about 13.5 percent of the worldwide total) and 92 million disability-adjusted life years (DALYS) -- 6 percent of the worldwide total -- among people over age 30 were caused by high blood pressure in 2001.
About 54 percent of strokes and 47 percent of heart disease cases were attributed to high blood pressure. About half of those cases occurred in people with hypertension (greater than 140 mm Hg systolic), while the remainder occurred in people with lesser degrees of high blood pressure.
In high-income countries, the proportion of premature deaths due to high blood pressure was 17.6 percent, compared to 12.9 percent in middle- and low-income nations. The proportion of DALYS due to high blood pressure in high-income nations was 9.3 percent, compared to 5.6 percent in middle- and low-income nations.
However, 80 percent of worldwide high blood pressure-related deaths occurred in middle- and low-income nations in eastern Europe and Asia, including China and India. More than one-third of all deaths in lower-income nations in Europe and central Asia were related to high blood pressure.
In high-income countries there were 1.39 million high blood pressure-related deaths; 418,000 stroke deaths; 668,000 heart disease deaths; 109,000 deaths due to hypertensive disease; and 197,000 deaths due to other cardiovascular diseases.
In low- and middle-income countries, there were 6.22 million high blood pressure-related deaths: 2.5 million stroke deaths; 2.68 million heart disease deaths; 598,000 hypertensive disease deaths; and 445,000 deaths due to other cardiovascular diseases.
"Most of the disease burden caused by high blood pressure is borne by low-income and middle-income countries, by people in middle age, and by people with lesser degrees of high blood pressure. Prevention and treatment strategies restricted to rich countries or individuals with hypertension will miss much blood pressure-related disease," wrote the University of Auckland researchers.
The study is published in this week's issue of The Lancet.
"Middle-income countries and low-income regions have a five times greater burden of disease than high-income regions, with access to less than 10 percent of the global treatment resource... This travesty cannot continue to be ignored by those most able to bring about change," Stephen MacMahon, of the George Institute for International Health at the University of Sydney in Australia, and his international colleagues, wrote in an accompanying editorial.
More information
The American Heart Association has more about high blood pressure.
Wednesday, February 06, 2008
Born to Be Obese?
(HealthDay News) -- The brain circuitry that controls appetite might be wired differently in some people, and that could predispose them to obesity, California researchers suggest.
The study was conducted in rats, not humans, and yet it could ultimately lead to novel obesity treatments, said Philip Smith, director of the Office of Obesity Research at the National Institute of Diabetes and Digestive and Kidney Diseases.
"It is not just about drugs that modify short-term appetite," he said, "there may be drugs that stimulate development of the appropriate neural pathways. So, it is an exciting, but very early, time in this field."
The study was published in the February issue of Cell Metabolism.
Sebastien Bouret, an assistant professor of neuroscience at the University of Southern California, and his colleagues examined neural circuits emanating from the appetite, hunger and body-weight control center of the brain -- the so-called arcuate nucleus of the hypothalamus (ARH) -- in a series of rats bred to be either prone to, or resistant to, obesity.
The team found fewer neural connections projecting from the ARH in obesity-prone animals than in their leaner counterparts. Surprisingly, Bouret said, this deficiency developed very early in life, before the animals became obese, and appeared to extend into adulthood.
"Somehow, these animals are programmed to become obese," Bouret said. "The obesity is hard-wired into the brain."
When the researchers then looked at why the brains of obese rats differed from their normal-weight counterparts, they found that the neurons from obesity-prone animals were less responsive to leptin, a hormone that controls the development of these circuits, and which also signals the body's energy status and controls metabolic rate.
"This paper presumes to say, these animals must be leptin-resistant, and that is why the pathways are not developing," said Smith.
But that doesn't mean they are doomed to a life of severe obesity, said Dr. Barbara Kahn, chief of the Division of Endocrinology, Diabetes and Metabolism at Beth Israel Deaconess Medical Center, in Boston. How they live their lives also matters.
"It is important not to 'blame' the obese person or imply that he/she is responsible for being obese," Kahn noted. "Having said that, reasonable, healthy caloric restriction and a safe and sustainable program of physical activity can help limit weight gain and often bring about some degree of weight loss. In addition, healthy eating and regular exercise can reduce the complications of obesity such as type 2 diabetes and cardiovascular disease."
At the same time, she added, not everyone can wear a size 4.
"There is a certain aspect of genetics that sets somebody in a certain range of possible body weights, and then how that person lives his or her life will determine whether they are at the bottom or top of the range," she explained.
Human obesity has both genetic and environmental roots. The rats used in this study, like most humans, developed obesity when fed a high-energy diet. On a normal diet, they were heavier than normal rats, but not yet obese.
"This is quite an exciting paper," said Smith, "because it links more closely to human behavior than most rodent models we have seen."
The findings also suggest a possible therapeutic approach to combating human obesity. If drugs could be designed to influence the formation of neural circuits during development and targeted to at-risk pregnancies, Smith said, "there is a good likelihood we could have successful interventions that improve the health of the mother, and which have a major impact on disease risk for the infant, during pregnancy."
A related study from Boston University researchers in the same journal found that bulking up muscle mass can lead to a general metabolic improvement in obese individuals. "Interventions designed to increase skeletal muscle mass in at-risk human populations may prove to be critical weapons in the fight against obesity and obesity-related comorbidities, including diabetes, heart disease, stroke, hypertension and cancer," an accompanying editorial stated.
More information
For more on obesity, visit the National Institute of Diabetes and Digestive and Kidney Diseases.
Sunday, September 30, 2007
Weight Loss Can Control Hypertension
(HealthDay News) -- An Italian study has identified overweight as a direct cause of high blood pressure. And it also showed that up to half of overweight people can bring down blood pressure to healthy levels by weight reduction.
But the weight loss has to be achieved before the borderline to outright obesity is crossed, said Dr. Roberto Fogari, professor of medicine at the University of Pavia. He was to present the study findings Friday at the annual meeting of the American Heart Association's Council for High Blood Pressure Research, in Tucson, Ariz.
It's important that the study linked overweight to high blood pressure, which usually is described as "essential," a medical term meaning that the cause is unknown, Fogari said.
"The study suggests that, in many cases, hypertension [high blood pressure] is not essential," he said. "It is secondary to overweight. So, in the first stages of overweight, if we can induce people to reduce overweight, they can also avoid being treated for hypertension."
The study included 210 men and women whose body mass index [a ratio of weight to height] was between 25 and 29.9, indicating overweight but just short of the 30 mark of obesity. Their systolic blood pressure was between 140 and 159, and their diastolic pressure was between 90 and 99, indicating moderately high blood pressure.
An individualized low-calorie diet was designed for each study participant. Some also were prescribed orlistat, a drug that prevents fat from being metabolized.
After six months, 53 percent of the men and 49 percent of the women in the study achieved normal body weight, and a 5 percent reduction in blood pressure.
"The other 50 percent of those in the study already had abnormal changes in the vascular tree [blood vessel system], so that hypertension was no longer reversible by losing weight," Fogari said.
The implication for practicing physicians who see moderately overweight people with high blood pressure is that their first goal should be weight reduction, he said.
"Only after six months of trying to reduce the patient's weight can a decision be made about drug treatment," Fogari said.
Dr. Daniel W. Jones, dean of the University of Mississippi School of Medicine, and a spokesman for the American Heart Association, said the study finding "is not new news, but it is important news."
There have been a number of previous studies showing that weight loss can reduce blood pressure, Jones said. "But this is an increasingly important problem in societies around the world," he said. "Once you gain weight, you find it difficult to lose weight, which is why we focus so much on preventing obesity these days."
As for drug treatment of high blood pressure, about half of California adults diagnosed with hypertension do not take medication for it, another report presented at the same meeting found.
The study of 11,467 persons given a diagnosis of hypertension found that 49.4 percent were not taking drugs to reduce their blood pressure, said the report by researchers at the California Department of Public Health's Heart Disease and Stroke Prevention Program.
There were some bright spots in the picture. Compliance was more than five times higher for those who had seen a doctor in the past year than for those who had not. And the compliance rate was twice as high for persons with health insurance than the uninsured.
More information
For more on high blood pressure and what to do about it, turn to the American Heart Association.
Sunday, July 29, 2007
Blood Pressure Drop During Bypass Might Impair Thinking
(HealthDay News) -- Patients who experience a blood pressure drop during bypass surgery may be at increased risk for a short-term dip in their cognitive abilities.
Researchers at the Johns Hopkins University School of Medicine in Baltimore studied 15 patients, aged 57 to 81, who were given cognitive tests before and then three to five days after they had coronary artery bypass graft (CABG) surgery.
All the patients had a decrease in mean arterial pressure (MAP) during surgery compared with their MAP before surgery. MAP provides doctors with an estimate of the blood pressure in various organs in the body.
The study found that patients whose MAP decreased by 27 millimeters of mercury or more had an average decrease of 1.4 points (out of a maximum of 30 points) on a standard cognitive test. Patients with a MAP decrease of less than 27 millimeters of mercury increased their scores by an average of one point.
Patients with a high MAP before their surgery were more likely to score lower on the cognitive test after their surgery.
The researchers also used MRI to examine the brains of 13 of the patients. They found that patients whose MAP decreased by more than 27 millimeters of mercury were 2.7 times more likely to show evidence of acute stroke.
The study was published online this week in the Archives of Neurology and is expected to be published in the August print issue.
The preliminary data from this small study suggests "that a substantial decrease in MAP from a patient's baseline may be a risk factor for short-term cognitive dysfunction," the study authors wrote. "This may be in part because of an increased risk for radiographic stroke."
Further studies are needed, the researchers said.
More information
The Alzheimer's Association has more about mild cognitive impairment.
Thursday, July 05, 2007
Don't Get Burned by Heat Stroke
(HealthDay News) -- Staying cool on hot summer days isn't just comfortable, it could save your life, according to the Pennsylvania Medical Society.
Heat stroke -- injury to internal organs caused by an excessively high body temperature -- is a serious and potentially deadly illness that can usually be prevented. Even so, it still happens all too frequently, experts say.
Many people recall the August 2001 death of Minnesota Viking's football player Korey Stringer.
He died after developing multi-organ system failure on a hot day. Athletes are particularly vulnerable to heat stroke -- especially football players, who wear body-covering uniforms and practice in the hottest temperatures -- but it can affect anyone.
Heat stroke can occur when you are in an extremely hot environment for a long period of time. It also happens when people overexert themselves on very hot days.
According to the Pennsylvania Medical Society, you should be alert to heat stroke on days when the relative humidity is at least 70 percent and temperatures are 95 degrees Fahrenheit and higher.
Other heat-related afflictions that may be a sign of looming heat stroke include heat cramps and heat exhaustion, which is characterized by pale, moist skin; headache; dizziness; nausea;
increased heart rate; low blood pressure; elevated temperature and profuse sweating.
The symptoms of heat stroke are more severe than those of heat exhaustion and may include:
Initial profuse sweating.
Hot, dry red skin.
High fever.
Vomiting.
Confusion.
Seizures during cooling.
Unconsciousness.
Sometimes lack of sweating, though athletes may perspire.
High body temperature (often 105 degrees or higher).
Anyone experiencing these symptoms should immediately seek emergency medical help.
Steps you can take to keep cool despite hot temperatures include:
Avoid overexertion.
Drink a quart of fluids an hour.
Wear loose, light-colored clothing made of light fabrics.
Wear a hat and sunblock.
Stay in the shade or indoors when possible.
Open windows and use fans and/or air conditioning; if you don't have air conditioning, go to a public place that does (a mall, library or movie theater).
Avoid dehydrating beverages such as caffeine and alcohol.
More information
The U.S. Centers for Disease Control and Prevention has more about extreme heat.
Friday, April 06, 2007
Added Pounds Mean Added Risk for Asthma
 (HealthDay News) -- Overweight and obese individuals are 50 percent more likely to develop asthma than normal-weight men and women, new research suggests.
Public health efforts to control asthma should therefore emphasize the importance of healthy weight management, the researchers argue in the April issue of the American Journal of Respiratory and Critical Care Medicine.
"The bottom-line is that being overweight appears to significantly increase the risk of asthma," said study co-author Dr. E. Rand Sutherland, of the National Jewish Medical and Research Center (NJMRC) in Denver. "But the caveat is, that until further studies are done, it won't be clear exactly what type or severity of asthma is present in obese people."
According to the U.S. National Institutes of Health, asthma is an incurable but usually controllable chronic disease involving inflammation and narrowing of the airways that carry oxygen into and out of the lungs.
The disease typically provokes recurrent wheezing, coughing, and a hypersensitivity to allergies and affects approximately 20 million Americans, including 9 million children.
A recent national survey found that about 65 percent of Americans are either obese or overweight, and research has long suggested links between asthma and obesity.
In this study, Sutherland and NJMRC colleague Dr. David A. Beuther pored over prior data on the body mass indices -- measurements of body fat based on the height and weight -- of adult asthma patients.
They looked at data from seven prior studies conducted between 1966 and 2006 in the United States, Canada, and Europe. Together, these studies had looked BMI and asthma in more than 333,000 severely asthmatic patients.
During data review, Sutherland and Beuther adopted standard BMI yardsticks, which define "normal weight" as having a BMI of under 25, "overweight" as a BMI between 25 and 29, and "obese" as a BMI more than 30. For example, a person who is 5 feet 6 inches tall and weighs 145 pounds has a BMI of 22.
The odds of developing asthma grew by 50 percent among patients with a BMI of 25 and up, and the risk climbed as the pounds piled on, the study found.
Women and men appeared to be equally susceptible to the weight-asthma association, they added.
Based on the findings, the researchers believe asthma should be added to the long list of diseases -- including diabetes, sleep apnea, stroke, cardiovascular illness, and arthritis -- for which excess weight is a risk factor.
And because two-thirds of the U.S. adult population are now thought to be obese or overweight, that means millions more Americans may be at risk of developing asthma than was previously thought, they said.
On the up side, "significant weight loss" could potentially reduce asthma cases by as many as 250,000 each year, the researchers said.
Not every overweight person with respiratory symptoms necessarily has asthma, however. The experts noted that excess weight can cause lung volume reduction, chest wall restriction, and breathlessness unrelated to the disease.
"If you're overweight, and you have respiratory symptoms, you don't need to jump to the conclusion that you have asthma," said Sutherland. "But, of course, it would probably be appropriate to have those symptoms further evaluated."
Dr Norman H. Edelman is chief medical officer for the American Lung Association and professor of preventive medicine and medicine at Stony Brook University in Stony Brook, N.Y. He said the findings regarding gender were most interesting.
"There's a lot of work that suggested the [obesity] effect was there in women and not in men," he said. "Certainly, in terms of my own clinical practice, I see people -- men and women -- with asthma that's difficult to manage, and many of them are overweight. But for men, it's something that wasn't clear before, and that's why this analysis is valuable."
But he agreed that proving cause and effect is tricky.
"The problem with asthma is that, unlike many other diseases, it's not like flipping a switch. It's not that you have it or don't have it. There are a lot of people walking around with a little bit of asthma, and they don't even know it," Edelman said. "So, it's not clear if obesity is actually causing the disease or perhaps converting a pre-existing undiagnosed asthma into a severe asthma. So, I don't know if I would say that obesity causes asthma. But certainly, it's a risk factor for clinically significant asthma."
More information
For more on asthma, visit the U.S. National Institutes of Health.
Friday, March 30, 2007
Physical Activity Cuts Risk of Repetitive Strain Injury
(HealthDay News) -- Being physically active may reduce the risk of repetitive strain injuries at work, according to a new Canadian study.
Researchers at the University of British Columbia in Vancouver analyzed data from the 2003 Canadian Community Health Survey. They found that the overall prevalence of repetitive strain injury (RSI) was about 10.9 percent, and that the prevalence of work-related RSI was about 4.7 percent. Upper body injuries (most commonly wrist/hand, shoulder and elbow) accounted for 63 percent of RSI in full-time workers.
Physical work demands, work-related stress, obesity, and smoking were among the risk factors associated with upper-body work-related RSI, the study said. Women and people ages 30-49 were also at higher risk. Being physically active appeared to help reduce the risk of work-related RSI.
"This finding provides evidence for a hypothesis that an active lifestyle outside of work may protect against work-related RSI, adding another potential health benefit to leisure-time physical activity participation," the study authors wrote.
Physical activity may promote mechanical and metabolic processes in the musculoskeletal system that counter the repetitive or sedentary effects of many jobs, the researchers said. It may also improve upper body muscle strength and better balance of movement.
"Work-related RSI is a common problem that has significant costs in terms of lost wages and productivity, medical care and quality of life," the study authors wrote. "It is important to identify lifestyle factors that may protect against RSI in order to inform employers, compensation boards, and the working population. Identification of safe physical activities may reduce RSI and provide multiple other health benefits."
The findings are published in the April issue of the journal Arthritis Care & Research.
More information
The U.S. National Institute of Neurological Disorders and Stroke has more about repetitive motion disorders.
Wednesday, March 14, 2007
Women Benefit Less From Clot-Busting Stroke Drug
(HealthDay News) -- Women who suffer strokes are much less likely than men to benefit from treatment with the powerful clot-dissolving drug known as tissue plasminogen activator (tPA), new research suggests.
The biggest such study yet conducted found that while more women survived their stroke after receiving tPA, male patients were more than three times as likely to retain good physical function as measured by a test three months after tPA treatment.
"The most intriguing possibility is that there might be an intrinsic biological difference in the way in which women respond to tPA vs. how men respond to tPA," said Dr. Gary Abrams, an associate professor of neurology at the University of California, San Francisco, and a spokesman for the American Academy of Neurology.
Abrams was not involved in the study, which is published in the March 13 issue of Neurology.
Federal rules mandate that tPA can be used only if treatment starts in the first three hours after a stroke. The drug helps limit brain damage by dissolving clots that block blood flow through arteries.
The trial included almost 1,400 stroke patients, 333 of whom (24 percent) were treated with tPA within three hours.
The study found that 47.5 percent of men getting tPA had good function three months later on a standard measure called the Barthel Index, compared to 30.3 percent of women. On another measure, the Rankin Score, 32.2 percent of men and 23.4 percent of women did well.
"In general, women have worse outcomes than men after a stroke," noted lead researcher Dr. Mitchell S. V. Elkind, an associate professor of neurology at Columbia University, in New York City. "There are potential biological reasons why women may not respond as well as men to tPA. Hormonal factors such as the effects of hormones on blood clots may be the reason."
But Elkind added that, "at this point in time, it is premature to treat women differently [than men] after a stroke. We recommend that women as well as men get to a hospital as quickly as possible and be treated as aggressively, including tPA."
There have been indications that postmenopausal women have higher levels than men of a substance that inhibits tPA activity, Abrams said. "A lot more work would have to be done to prove it, but it is an intriguing thought. But there is conflicting evidence and reasons to believe there are caveats in taking this too far."
The results should also be interpreted cautiously, noted Dr. Edgar J. Kenton III, chair of the American Academy of Neurology's practice committee. "This is the only large trial of the response to tPA in women," he said. "We need more trials proving the point one way or another."
"I don't want this study interpreted to say that women should not get tPA," Kenton stressed. "There are small studies suggesting that with ultra-early treatment -- within one hour -- they do better than men. We need more women in more trials to look at these factors."
Kenton also noted the unusually high percentage of patients in the study who received tPA therapy within the three-hour post-stroke limit recommended by experts.
"Twenty-four percent got tPA within three hours," Kenton noted. "The national average is 5 or 6 percent." The measures used in this trial to get tPA delivered to patients early can and should be applied to everyday practice, he said.
More information
Find out more about tPA at the American Heart Association.
Friday, February 02, 2007
The Cardiovascular Cure: How to Strengthen Your Self-Defense Against Heart Attack and Stroke - Book Review
BY JOHN P. COOKE, M.D., PH.D., AND JUDITH ZIMMER; B
ROADWAY BOOKS; $25
SOME MAINSTREAM DOCTORS are bucking the system and suggesting that surgery or drugs may not be the best treatment for stroke, heart disease, and atherosclerosis (hardening of the arteries). One of these doctors, John P. Cooke, M.D., Ph.D., director of the vascular medicine section at Stanford University Medical School in Palo Alto, Calif., has written a book to help us trigger our body's remarkable capacity to heal itself.
Cooke and co-author medical journalist Judith Zimmer explain that a healthy endothelium, the innermost single-cell-thick lining of human blood vessels, releases a substance that packs benefits galore. Called nitric oxide (NO), this substance keeps blood vessels supple, prevents platelets from snagging on vessel walls, hinders the buildup of plaque, and even helps to reduce existing plaque deposits. Cooke says people with heart disease or the risk factors for it have elevated levels of an amino acid that impedes NO production.
To ensure that your endothelium pumps out plenty of NO, Cooke recommends a modified Mediterranean-style diet supplying 1,800 calories a day. The evidence-based diet features whole grains, beans, nuts, legumes, fruits, and vegetables, and emphasizes foods rich in L-arginine, an amino acid used by the endothelium to make NO. His book includes a two-week eating plan with recipes, and detailed information on supplemental nutrients and phytochemicals.
The other component of Cooke's simple plan is aerobic exercise, which increases blood flow through your vessels. Increased blood flow stimulates the production of NO and keeps the endothelium smooth so plaque accumulation is less likely. He advocates at least 30 minutes of aerobic exercise four days a week.
This book manages to be both comprehensive and lively. Cooke presents just the right amount of detail about the scientific underpinnings of his conclusions, which are based on a Nobel-prize-winning theory. He claims you will have vascular improvement in just two weeks--and I believe him.
COPYRIGHT 2002 Weider Publications
COPYRIGHT 2002 Gale Group
The Cardiovascular Cure
The Cardiovascular Cure
Written by John P. Cooke, M.D., Ph.D. and Judith Zimmer
Category: Medical - Diet Therapy
Publisher: BroadwayFormat: Trade Paperback, 336 pagesPub Date: August 2003
Price: $15.95
ISBN: 978-0-7679-0882-5 (0-7679-0882-1)
ABOUT THIS BOOK
The Cardiovascular Cure offers a groundbreaking approach to preventing heart attack and stroke by enhancing your body’s own natural defenses. Dr. John Cooke, head of Stanford Medical School’s vascular unit, has devised a powerful new method for fighting cardiovascular disease without bypass surgery or angioplasty.
Drawing on his own investigations, as well as Nobel Prize-winning research from a team of American scientists, Dr. Cooke provides heart patients with a diet, supplement, and exercise program that will help them feel better in as little as two weeks.
His program also works to prevent heart disease in those at risk.
In 1998, the Nobel Prize in Physiology or Medicine was awarded for the discovery of EDRF (endothelium-derived relaxing factor), a chemical produced in the lining of the blood vessels, which keeps them free of plaque. Dr. Cooke and other investigators have found that specific nutrients can enhance EDRF production and improve blood flow in people with high cholesterol, high blood pressure, diabetes, or other risk factors for heart disease.
This potentially life-saving book shows how anyone can achieve healthier blood vessels (the key to preventing heart disease). A two-week menu plan contains recipes that emphasize EDRF-enhancing foods, and there is detailed information on supplemental nutrients and vitamins that are useful in strengthening the cardiovascular system. Recipes from breakfast (Banana Date-Nut Bread; Blueberry Oat Pancakes; Pineapple Ginger or Tropical Smoothies; Pumpkin Muffins) to dinner (Moroccan Red Snapper; Chicken Wrap with Refried Beans; Soy-Glazed Salmon; Turkey Meatloaf) feature healthy fats found in fish, nuts, and olive oil.
There is also welcome news that red wine and chocolate can be good for you (there are recipes for Double Chocolate Cake and Chocolate Raspberry Surprise). The exercise program consists of the same therapeutic plans Dr. Cooke has prescribed for even his most severely ill patients, many of whom begin to walk and even exercise more vigorously without pain after two weeks. In addition, there are aerobic workouts designed for more active patients.
Dr. Cooke also provides state-of-the-art information (pro and con) on conventional drugs–from aspirin to beta blockers–and medical tests and procedures to further combat cardiovascular disease. With an introduction by Sir John Vane, a Nobel Prize-winning cardiovascular scientist, this book will provide anyone concerned about his or her cardiovascular health with new hope for a pain-free, disease-free life.
From the Hardcover edition.PRAISE“In The Cardiovascular Cure, Dr. Cooke has translated the research of our field into life-saving information that we can all use. If you really care about your cardiovascular health, you must read this book!”--Louis J. Ignarro, Ph.D., 1998 Nobel Laureate in Physiology or Medicine for the discovery of Nitric Oxide“This authoritative book appropriately points out why everyone should worry about the health of their endothelium and, better still, do something to protect it if it shows signs of damage.
Early identification and treatment of reduced nitric oxide release should be the preventive agenda for the new millenium.”--Jay N. Cohn, M.D., Professor of Medicine, University of Minnesota Medical School“This book should be read by all patients with heart disease as well as anyone at increased risk for a heart attack or stroke.
The comprehensive risk reduction program recommended by Dr. Cooke uses the most advanced research to help everyone improve the health of their blood vessels.” --William L. Haskell, Ph.D., Stanford Center for Research in Disease Prevention“The Cardiovascular Cure is a lucidly written description of EDRF and endothelial dysfunction.
Treatment with exercise and a diet rich in arginine, vitamins, and anti-oxidants is important to the many patients prone to develop heart attacks or stroke.”--Dr. Ferid Murad, M.D., Ph.D., Director of the Institute of Molecular Medicine at the University of Texas, 1998 Nobel Laureate in Physiology or Medicine“Helping yourself prevent a heart attack means knowing more than your ‘cholesterol count.’
In this clearly written book, Dr. Cooke introduces you to the important role played by the endothelium (the lining of your blood vessels) in this process, and what you can do to keep this vital organ as healthy as possible.”--Gerald Reaven, Professor of Medicine, Stanford University School of MedicineFrom the Hardcover edition.
ABOUT THIS AUTHORJOHN P. COOKE, M.D., Ph.D., is Associate Professor of Medicine and Director of the Section of Vascular Medicine at Stanford University’s Medical School. He trained at the Mayo Clinic, earning a Ph.D. in physiology there, and he was on the faculty of Harvard Medical School before he was recruited to Stanford to spearhead the program in Vascular Biology and Medicine.
He is a sought-after consultant and has served on numerous national and international committees dealing with cardiovascular diseases, including those of the American Heart Association and the National Heart, Lung and Blood Institute. JUDITH ZIMMER has been a medical journalist for more than fifteen years.
She has contributed to such publications as the New York Times, and Self and Fitness magazines, and she currently writes for academic medical centers in New York City.
From the Hardcover edition.
Wednesday, January 10, 2007
Psychological Interventions Ease Chronic Low Back Pain
 (HealthDay News) -- Psychological treatments such as hypnosis, biofeedback, relaxation and counseling can help relieve chronic low back pain, according to a review in the January issue of the journal Health Psychology.
U.S. researchers examined the findings of 22 studies of patients with low back pain conducted between 1982 and 2003 and concluded that psychological treatments not only improve health-related quality of life and lower the risk of depression, they also reduce patients' experience of pain.
"Because this analysis was both more inclusive and more conservative than previous reviews, we have the best evidence to date that these interventions are helpful," review lead author Robert Kerns, of the VA Connecticut Healthcare System, said in a prepared statement.
Kearns said he and his colleagues were somewhat surprised by the finding that psychological treatments can reduce pain. That's because when psychologists first started to develop these kinds of treatments several decades ago, the objective was to help patients cope with their pain, not to actually lower their pain levels.
"However, a growing body of knowledge suggests that these interventions are actually having a primary effect on people's experience of pain," Kearns said.
The review found that of all the psychological interventions, cognitive-behavioral and self-regulatory treatments seemed to provide the greatest benefits to patients with low back pain.
"Psychological interventions are not cures, but they do reduce pain and improve function, and they are important components in the treatment of people with chronic pain," Dennis Turk, professor of anesthesiology and pain research at the University of Washington in Seattle, said in a prepared statement.
More information
The U.S. National Institute of Neurological Disorders and Stroke has more about low back pain.
Friday, December 01, 2006
FDA Panel Backs Celebrex for Kids With Arthritis
(HealthDay News) -- A U.S. Food and Drug Administration advisory panel recommended Wednesday that use of the painkiller Celebrex be expanded to treat children with juvenile rheumatoid arthritis.
The panel, a committee of doctors and other specialists, voted 15-1 that the benefits of the drug for children with juvenile rheumatoid arthritis (JRA) outweigh the shortage of proof on its safety.
However, the panel also voted 8-7, with one abstention, that available data doesn't demonstrate that Celebrex is safe in treating JRA and that a registry should be established to track these young patients for 10 to 20 years.
"The feeling was short-term efficacy looked good and short-term safety was not an issue. Long-term safety is totally unknown and needs to be known," Dr. Joan Bathon, a Johns Hopkins University rheumatologist and panel member, told the Associated Press.
"That's not unreasonable. But the important part, when they considered both safety and benefit, is the benefits outweighed the risks," Dr. Steven Romano, a vice president in Pfizer's worldwide medical division, told the AP.
"This decision means that one additional therapeutic choice is available for patients and doctors," Dr. Jeffrey Greenberg, director of the Arthritis Translational Research Registry at New York University Hospital for Joint Diseases, told HealthDay.
"Any unknown, long-term cardiovascular risk associated with the use of Celebrex will need to be factored into the decision," he added.
The FDA is not required to follow the recommendations of its advisory committees, but it usually does.
It's estimated that as many as 60,000 children in the United States have JRA, which causes painful joint swelling and can affect growth and development.
Currently, Celebrex is approved to treat adults with osteoarthritis and rheumatoid arthritis. In its application to expand that approval to include treatment of JRA, drug maker Pfizer Inc. included a six-month study that concluded that Celebrex (celecoxib) works as well as naproxen in treating young JRA patients.
Bathon said that the panel recognized the importance of expanding the pool of treatment options for JRA. Vioxx, until it was withdrawn in 2004, had been the only FDA-approved drug of its class for the disease.
Celebrex is a member of the controversial group of painkillers called cox-2 inhibitors, which have been linked to an increased risk of heart attack and stroke.
Two other cox-2s, Vioxx and Bextra, have been withdrawn from the market because of heart risk concerns. Celebrex remains available to consumers, but in 2005, the FDA required that the drug carry a "black box" warning on the possible risk of heart attack or stroke.
During public testimony before the advisory committee Wednesday morning, a New Jersey father said Celebrex had worked wonders for his son, who suffers from juvenile rheumatoid arthritis.
Vincent Del Gaizo, of Whitehouse Station, told the panel members that his son Christopher, now 6, had been in such pain from the disease and was taking so many drugs, he could only sleep three hours a day. Each morning, the boy sat in a high chair with his arms raised for hours because it hurt too much to lower them, the Boston Globe reported.
"It's an image that will be burned in my mind forever," said Del Gaizo, 38. The boy's doctor had "the courage" to try Celebrex "off-label," and now Christopher is able to play soccer and T-ball, his father said.
Also Wednesday, British researchers said they've discovered why Vioxx and other cox-2 inhibitors can cause heart attacks and strokes, BBC News reported.
The reason: These drugs -- designed to block the cox-2 enzyme and halt production of hormones that swell joints and cause pain in people with arthritis -- also stop an enzyme called cox-1 from producing blood-thinning agents. This results in a greater risk of blood clots, the news service reported.
The researchers said their findings are significant because they may lead to the development of cox-2 inhibitors that do not increase the risk of heart attack and stroke.
The findings were published in the Federation of American Societies for Experimental Biology Journal.
More information
For more on with juvenile rheumatoid arthritis, visit the U.S. National Library of Medicine.
Thursday, November 16, 2006
How old is your heart?
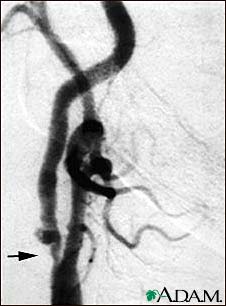 It is well known that cardiovascular disease is the #1 cause of death and disability in the Western World.
- Nearly 62 million Americans have at least one type of cardiovascular disease: Arteriolosclerosis (hardening of the arteries) and high blood pressure are the leading risk factors.
Every 29 seconds, an American has what doctors call a coronary event.. . .such as a heart attack
- Death occurs from a coronary event every minute.
- A death occurs from a stroke every 3 minutes.
Saturday, November 04, 2006
Regular Exercise Helps Obese Teens' Hearts
 (HealthDay News) -- Obese teens who start a regular exercise program can reverse or reduce early signs of heart disease, new research shows.
The finding suggests that continued exercise could decrease their risk of developing hardening of the arteries, heart attacks and strokes, said Dr. Andreas Alexander Meyer, of the University of Rostock in Germany.
"Obese young adults who were already obese in childhood have a high risk of developing serious cardiovascular events," Meyer said. "First events can occur between the age of 20 and 30 years."
Meyer's team studied 67 obese German teens with early signs of hardening of the arteries: decreased flexibility of their arteries and increased thickness in the linings of the carotid arteries of the neck.
"It was in the range we usually see in adults between the ages of 30 and 40," Meyer said. "This is clear evidence of vascular changes in obese children."
During the study, the researchers randomly assigned the teens, who averaged 15 years of age, to either a six-month exercise program or no change in their usual routine.
The exercise regimen included 60 minutes of swimming and water aerobics on Mondays, 90 minutes of team sports on Wednesdays and 60 minutes of walking on Fridays.
In the exercise group, the researchers saw an almost complete restoration of the arteries' flexibility, which resulted in improved blood flow. They also observed a significant reduction in the thickness of the linings of the youths' carotid arteries.
Because exercise also led to improvements in body-mass index (BMI), blood pressure, and cholesterol and triglyceride levels, the researchers concluded that it could significantly reduce the teens' risk of developing heart disease. "Even children who did not lose weight showed improvements in vascular status and obesity-related risk factors," Meyer said.
The study results are published in the Nov. 7 issue of the Journal of the American College of Cardiology.
Meyer cautioned that these benefits would quickly vanish if the teens did not maintain their healthy new lifestyle and strive to become even more physically active. "Generally, in children, we recommend moderate exercise of 45-90 minutes per day to keep cardiovascular risk low," he said.
Parental support is essential, Meyer said, but it can be difficult to convince parents -- who may themselves be obese and sedentary -- that their children's lives depend on eating right and exercising regularly.
"Most obese children don't get sufficient support in their efforts to reduce weight," Meyer said. "We have intensive talks with the parents about their children's medical and vascular status. We try to make clear that the whole family needs to change its risky behavior."
In recent years, childhood obesity has become a worldwide epidemic, affecting an estimated 22 million children under age 5. In the United States, one-third of children are either obese or at risk of becoming obese, according to a 2006 federal report, Progress in Preventing Childhood Obesity: How Do We Measure Up?.
Between 2002 and 2004, the obesity rate for American children and teens increased from 16 percent to 17.1 percent and is expected to reach 20 percent by 2010, according to the report.
"All children and adolescents should engage in at least 60 minutes of physical activity on most, preferably all, days of the week," said Karen A. Donato, coordinator of the National Heart, Lung and Blood Institute's Obesity Education Initiative. She was not part of the study.
"According to the U.S. dietary guidelines for Americans, regular physical activity has been shown to reduce the risk of certain chronic diseases, including high blood pressure, stroke, coronary artery disease and type 2 diabetes," Donato said. "The National Institutes of Health has begun a national education program entitled We Can! (Ways to Enhance Children's Activity and Nutrition) to provide parents and primary caregivers of children with important information and tips on ways to increase physical activity in children and youth, as well as to decrease screen time, and eat a nutritious diet."
More information
For more on childhood obesity, head to the U.S. Centers for Disease Control and Prevention.
Monday, October 02, 2006
Blood Pressure Is Focus of New Web Site
 (HealthDay News) -- The NIHSeniorHealth Web site (www.NIHSeniorHealth.gov) now features updated information on high blood pressure, according to the U.S. National Institute on Aging.
The new high blood pressure topic on the site contains information about the prevention, detection, and treatment of high blood pressure. The site was designed especially for older adults by the National Institute on Aging and the National Library of Medicine, which are part of the U.S. National Institutes of Health.
High blood pressure is often called the "silent killer" because most people are not aware they have it. But while it usually does not cause symptoms, high blood pressure can lead to stroke, heart disease, kidney failure, and other health problems.
"High blood pressure is not a normal part of aging," said Dr. Elizabeth G. Nabel, director of the National Heart, Lung and Blood Institute, which developed the content for the site.
"You can prevent high blood pressure by maintaining a healthy weight; being physically active every day; eating more fruits, vegetables, whole grains and low-fat dairy foods; cutting down on salt and sodium; and drinking less alcohol" Nabel said. "If you have high blood pressure, you can lower it by making these lifestyle changes and, if needed, by taking medicine."
More information
The NIHSeniorHealth Web site has more about high blood pressure.
Tuesday, September 19, 2006
Palate Implants Improve Sleep Apnea
 (HealthDay News) -- A minimally invasive surgical technique that involves the insertion of small polyester rods into the soft palate may be an effective, long-term treatment for mild-to-moderate obstructive sleep apnea.
Dr. Regina P. Walker of the Hinsdale Medical Center in Hinsdale, Ill., and colleagues tested the Pillar procedure in 22 middle-aged patients, including 16 men and six women, with mild-to-moderate sleep apnea. Although some of the patients had previously tried a treatment called continuous positive airway pressure (CPAP), none had undergone any earlier surgery for their sleep apnea.
After 90 days, 17 of the subjects showed significant improvements in their snoring intensity, daytime sleepiness and apnea hypopnea index, a measure of breathing interruptions that occur during sleep. Most significantly, these results were sustained after 15 months, indicating that the improvements could be permanent, according to Walker.
Overall, the patients' apnea hypopnea index decreased from a mean of 19.5 to 13 events per hour after 90 days, and to 12.8 events per hour after 15 months.
Walker was expected to present the study at the 110th annual meeting of the American Academy of Otolaryngology-Head and Neck Surgery Foundation, being held Sept. 17-20 in Toronto, Canada.
"This is an important study," said Dr. Michael Friedman, chairman of head and neck surgery at Rush-Presbyterian-St. Luke's Medical Center in Chicago. "Sleep apnea is a huge problem affecting at least 12 million Americans. If you count very mild forms of sleep apnea, the number goes up to 50 million."
In sleep apnea, breathing stops or gets very shallow during sleep. Each pause in breathing typically lasts 10 to 20 seconds or more. These pauses can occur 20 to 30 times or more an hour. The most common type of sleep apnea is obstructive sleep apnea, according to the U.S. National Institutes of Health.
Even mild forms of sleep apnea can increase a person's risk of cardiovascular disease by five times, Friedman said. The condition is also associated with an increased risk of high blood pressure, weight gain, memory problems, depression and impotence.
Until the Pillar procedure was introduced about six years ago, patients with sleep apnea only had two treatment options: CPAP, a machine that keeps the airways open during sleep; and invasive surgery to remove excess tissue in the mouth and throat.
Although both treatments are effective, they have drawbacks, Friedman said. Because many patients are unwilling or unable to use a CPAP machine, compliance is only about 40 percent. And the results of invasive surgery tend to diminish after a year as tissues loosen and symptoms return, he said.
During the in-office Pillar procedure, patients receive a local anesthetic before several polyester rods are inserted into their soft palate. Pain is usually minimal and can be managed with over-the-counter medications.
Most patients can resume full activity the same day and return to their usual diets after a day or two. They usually can't even feel the implants after a week or two. Rarely, implants work their way to the surface and must be re-implanted, Friedman said.
It's not the rods themselves that tighten loose tissue and reduce symptoms of sleep apnea, but the scar tissue that forms around them. "Scar tissue tends to become more effective over time," Friedman said. "That's why this study is important, because it shows that the results are stable or even better after 15 months, whereas the results of invasive surgery drop off after a year."
Although most of the patients in Walker's study were overweight or mildly obese, the Pillar procedure isn't recommended for patients who are morbidly obese. Friedman estimated that up to 50 percent of sleep-apnea patients are candidates for the procedure, but said it probably would be a stand-alone treatment for only about half of them.
"The nice thing about this procedure is it doesn't eliminate the possibility of other procedures," Walker said. "Quite often, we can combine many treatments. Studies are now being done on implant patients who use CPAP machines to see if it's possible to reduce CPAP pressure."
The Pillar procedure costs about $1,500, which insurance may cover in patients with diagnosed sleep apnea but not in patients who simply have snoring problems. "It's still a fairly new procedure that doesn't have a specific CPT code," Walker said. "I would say that about 25 to 30 percent of procedures in sleep-apnea patients are being paid for, although the number appears to be increasing."
Some doctors are using the Pillar procedure to treat severe sleep apnea. "But this hasn't been well-studied," Walker said. "So, it's too early to say if the implants will be of benefit to such patients."
More information
To learn more about sleep apnea, visit the National Institute of Neurological Disorders and Stroke.
Subscribe to:
Posts (Atom)
Dr. Group's Secret to Health Kit$39.94  Dr. Group's Secret to Health Kit offers simple at-home solutions for cleansing internally and externally thereby reducing toxins, restoring the body's natural healing process, and helping you achieve true health and happiness. |